Emergency Dentist Solutions for Cracked Teeth After Biting Hard Foods

A cracked tooth rarely announces itself with drama. More often, it starts with a sharp, surprising sting while chewing on something that seemed harmless a second earlier, a crusty baguette, a handful of nuts, an olive pit hiding in a salad, a popcorn kernel that did not fully pop. You pause, test the tooth with your tongue, and wonder whether you chipped enamel or caused real damage. That moment matters more than most people realize.
Cracks after biting hard foods are one of the more common reasons patients seek an Emergency Dentist. The reason is simple: teeth are strong, but not indestructible. Even healthy teeth can fracture under the wrong force, and teeth that already carry fillings, root canal treatment, grinding wear, or hidden decay are more vulnerable than they appear. The challenge is that not every cracked tooth feels the same, and not every crack demands the same treatment. Some can be stabilized quickly and restored well. Others become emergencies because the crack exposes the nerve, destabilizes the tooth, or extends below the gumline.
Knowing what tends to happen next, and what an Emergency Dentist can realistically do the same day, can save a great deal of pain and sometimes save the tooth itself.
Why hard foods cause sudden fractures
Most people picture trauma as a fall, a sports collision, or a blow to the face. In practice, a large number of tooth fractures happen at the dinner table. Hard foods create intense, localized pressure. If that force lands on a cusp, the pointed chewing surface of a back tooth, it can split off a section of enamel and dentin in a fraction of a second.
Age plays a role. Teeth become more brittle over time, especially if they have large restorations or decades of grinding. So does anatomy. Molars absorb the bulk of chewing force, and they tend to crack more often than front teeth. A tooth with a deep filling may look serviceable on an X-ray and still be at risk because less natural tooth remains to support the bite. Patients are often surprised by this. They say the tooth never hurt before, which is true. A cracked tooth can be silent until the day it is not.
One pattern shows up repeatedly in emergency care: the patient bites down, feels a clean, stabbing pain, then notices two different sensations. First, pain when chewing. Second, sensitivity to cold or sweets that lingers longer than it used to. Those clues suggest the fracture may be more than superficial.
What a cracked tooth can feel like
Cracked teeth do not all produce constant pain. Some only hurt when pressure is applied in a specific direction. Others release pain when the bite is let go, a classic sign of movement along a crack line. Some feel rough but not painful because only a small corner broke away. Others throb because the pulp, the living tissue inside the tooth, is inflamed or exposed.
Patients describe it in very practical terms. One says, “It feels like the tooth opens when I chew.” Another says, “Cold water hits it and I jump.” Someone else notices a jagged edge slicing the side of the tongue. All three can represent different levels of urgency.
The tricky part is that a crack is not always visible in the mirror. Hairline fractures may hide inside the tooth or run between cusps. A dentist often needs magnification, special lighting, bite tests, percussion, and X-rays to form a complete picture. Even then, some cracks declare themselves gradually over days or weeks.
When it becomes a true dental emergency
Not every chip requires a same-day visit, but some symptoms should move the issue out of the “wait and see” category. An Emergency Dentist usually wants to see you promptly if the crack changes your bite, causes persistent pain, creates swelling, or exposes soft inner tooth structure.
Here are the signs that deserve quick attention:
- Pain when biting that is sharp, repeatable, or worsening
- Sensitivity to cold or heat that lingers after the stimulus is gone
- A visible missing piece of tooth, especially on a molar used for chewing
- Swelling of the gum, face, or jaw, or a bad taste that suggests infection
- A tooth that feels loose, uneven, or suddenly “high” when you close
A crack can be manageable in the morning and much worse by evening if a fragment shifts or the pulp becomes inflamed. That is why emergency dental teams take bite-related fractures seriously, even when the tooth looks only modestly damaged from the outside.
What to do before you reach the office
The period between the injury and the appointment can make the situation better or worse. The goal is to reduce pain, protect the tooth from additional stress, and avoid contaminating the area if the tooth is open.
Most people do best with a few basic steps:
- Rinse gently with lukewarm water to clear debris
- Avoid chewing on that side, and skip hard, sticky, or very hot and cold foods
- If there is swelling, use a cold compress on the outside of the face for short intervals
- Take an over-the-counter pain reliever if you normally tolerate it and your physician has not told you to avoid it
- If a sharp edge is cutting your tongue or cheek, cover it temporarily with sugar-free chewing gum or dental wax
A common mistake is trying to “test” the tooth repeatedly. People tap it, bite on it, or chew carefully to see whether it is really cracked. That usually adds irritation. Another mistake is putting aspirin directly on the gum. It does not treat the tooth and can irritate or burn soft tissue.
If a piece of the tooth breaks off cleanly and you can find it, bring it with you. It is not always reusable, but it can help the dentist judge the fracture pattern.
What an Emergency Dentist looks for right away
Emergency visits for cracked teeth are focused, but they are not casual. The dentist needs to answer several questions quickly. Is the crack limited to enamel, or does it extend into dentin or pulp? Has a cusp fractured off? Is the tooth restorable? Is the nerve inflamed, infected, or still calm enough to preserve? Has the crack crossed into the root, where the long-term outlook changes substantially?
The exam usually includes a clinical inspection, X-rays, bite tests, temperature testing, and evaluation of the gums around the tooth. If the tooth is heavily restored, the filling may need to be adjusted or partially removed to see what is actually happening. Some cracks only become apparent after old material is taken away.
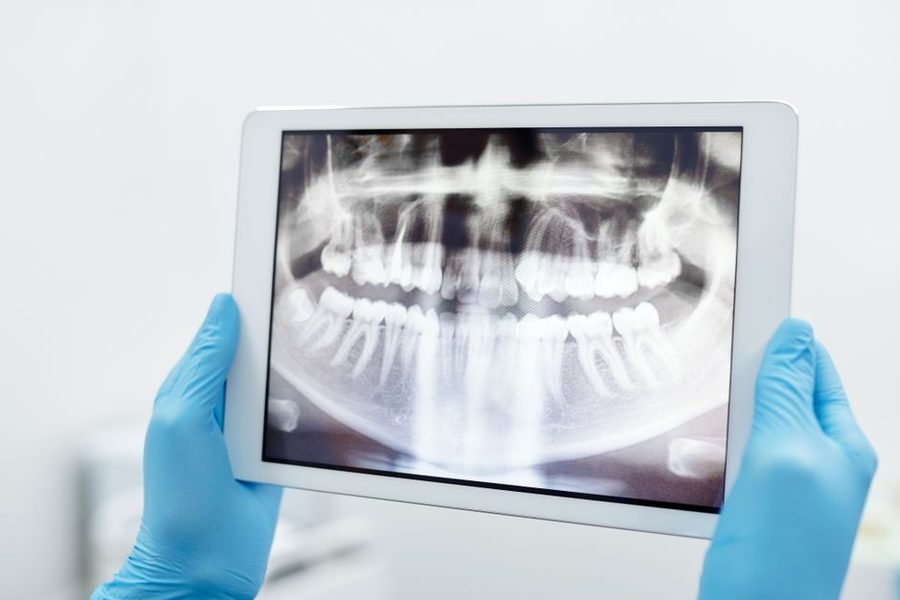
Patients often expect the X-ray to “show the crack.” Sometimes it does, especially if the fracture is large or the split involves the root. Very often it does not. Cracks are frequently narrower than what a standard dental X-ray can reveal. That is why symptoms and clinical tests matter so much.
An experienced Emergency Dentist also checks the bite pattern. A cracked tooth does not exist in isolation. If the patient clenches at night, has flattened chewing surfaces, or bites edge to edge, the repair plan may need to account for ongoing stress. Otherwise, even a well-done restoration can fail.
Same-day solutions that relieve pain and protect the tooth
The emergency solution depends on how far the damage goes. This is where judgment matters, because the goal is not just to patch a defect, but to choose a treatment that preserves the tooth without overpromising.
For a small chip limited to enamel, smoothing rough edges or placing a bonded filling may be enough. These cases often look dramatic to the patient because the edge feels sharp, but structurally they can be straightforward.
For a fractured cusp on a molar, the emergency visit may involve removing the unstable portion and placing a bonded restoration or a protective temporary build-up. If the nerve is not involved, this buys time for a full-coverage crown, which often becomes the definitive treatment. Crowns work well for cracked posterior teeth because they wrap the biting surface and reduce flexing under pressure.
If the crack has irritated the pulp but not destroyed it, the dentist may place a sedative dressing or temporary crown and monitor symptoms closely. This is a middle-ground scenario. Some teeth settle down after protection. Others declare irreversible pulp damage over the following days, especially if cold sensitivity starts lingering longer or spontaneous pain develops.
If the pulp is exposed or irreversibly inflamed, root canal treatment may be the best route to save the tooth. Many patients hear “root canal” and assume failure. In reality, a root canal can be the treatment that keeps a cracked but salvageable tooth functional for years, provided the crack does not extend too far below the gum or into the root in a way that compromises structural integrity.
When the crack splits the tooth vertically into separate segments, or runs deep below the gumline, extraction sometimes becomes the most predictable option. That is a hard conversation, but a necessary one. Trying to save a hopelessly cracked tooth can mean repeated pain, repeated cost, and eventual infection. Good emergency care includes honesty about limits.
The difference between a cracked tooth and a broken cusp
This distinction matters because patients often use the same language for both. A broken cusp is a portion of the tooth that fractures off, often around an old filling. It can be painful, but once the loose segment is removed and the tooth is covered, the prognosis may be quite good.
A cracked tooth, by contrast, often still looks mostly whole. The fracture line may run through the body of the tooth and open microscopically under pressure. These teeth can be harder to diagnose and sometimes less predictable. They may respond well to a crown if caught early, but the risk rises if symptoms have been present for a long time or if the crack extends toward the root.
From a patient’s perspective, both can start after biting hard food. From a treatment perspective, they are not the same problem.
How pain patterns help guide treatment
Dentists pay close attention to timing and triggers because they reveal what the nerve is doing. A brief zing to cold that fades quickly may point to exposed dentin but a still-recoverable pulp. Sharp pain on release after biting is strongly associated with crack movement. A dull, lingering ache that wakes someone at night raises concern for irreversible pulpitis, where the nerve is too inflamed to recover on its own.
There is also the issue of referral pain. Lower molars can make patients feel discomfort in the ear or jaw. Upper cracked molars sometimes produce vague sinus-like pressure. This is one reason people occasionally delay care. They assume they have sinus trouble, jaw strain, or generalized sensitivity when the source is actually one tooth.
A patient I once heard described by a colleague had chewed ice for years without trouble, then bit into a roasted almond and felt a flash of pain in a lower molar with an old silver filling. The tooth barely showed any visible https://www.behance.net/smyledbakersf change, but bite testing produced classic release pain. The cusp was intact, the crack ran under the old restoration, and the tooth was saved with prompt coverage. A few weeks’ delay could easily have shifted that outcome toward root canal treatment, or worse.
When a crown is enough, and when it is not
Patients often ask whether a crown “fixes” a crack. Sometimes yes, sometimes not. A crown does not erase a fracture line inside the tooth. What it does is splint the remaining structure and distribute biting forces more favorably. That can be enough when the crack is incomplete, the tooth is otherwise sound, and the pulp remains healthy or recoverable.
A crown is less likely to succeed on its own if the crack already involves the pulp deeply, extends below bone level, or travels down the root. In those cases, the issue is no longer just external reinforcement. It is internal damage and structural compromise.
This is where overconfident promises do patients a disservice. An experienced Emergency Dentist may say, in effect, “We can stabilize this today, but the long-term prognosis depends on what we find once the tooth is cleaned up and protected.” That answer may feel less satisfying than certainty, but it is the more professional one.
The role of temporary treatment
Temporary treatment is not second-rate care. In emergency dentistry, it is often the smartest first move. A provisional filling, temporary crown, bite adjustment, or sedative material can reduce movement, relieve pain, and create breathing room for a definitive plan.
This matters because cracked teeth can be diagnostically dynamic. A tooth that calms down after stabilization may avoid root canal treatment. A tooth that continues to throb, becomes sensitive to heat, or develops percussion pain may need endodontic therapy despite initial efforts to preserve the pulp.
Temporary treatment is especially useful when swelling, limited mouth opening, travel schedules, or insurance constraints make same-day definitive care impractical. The key is that “temporary” should come with clear follow-up, not quiet neglect.
What happens if you wait too long
Delaying care changes the biology and the mechanics. Cracks tend to propagate under repeated chewing. A small fracture becomes a larger one. The pulp moves from irritated to irreversibly inflamed. Bacteria gain access to deeper layers. A piece that might have been bonded becomes too compromised to restore.
Patients sometimes wait because the pain comes and goes. That pattern is common. Intermittent symptoms do not mean a crack is healing. Teeth do not knit back together like bone. If the symptoms disappear completely, it may even be because the nerve inside the tooth has died, which is not good news.
Another delayed-care problem is infection. Once bacteria travel into the pulp and out toward the root tip, swelling, abscess formation, and systemic discomfort can follow. At that point, treatment becomes more complex and often more expensive.
Cost, value, and the hidden expense of “just watching it”
People understandably think about cost when a tooth cracks unexpectedly. Emergency care can involve an exam fee, imaging, temporary stabilization, and then a final procedure such as a crown, root canal, or extraction with replacement. What matters is matching the spending to the actual prognosis.
For a restorable tooth, early treatment often costs less than waiting. A crown placed after a fractured cusp is typically less involved than a crown plus root canal after months of continued stress. On the other hand, if a crack clearly renders the tooth non-restorable, pouring money into heroic temporary measures rarely makes sense.
The useful question is not “What is the cheapest thing today?” It is “What is the most sensible path based on this tooth’s chance of long-term success?” Good dentists are willing to discuss that directly.
Preventing the next crack
Once someone has fractured a tooth on hard food, prevention becomes more than generic advice. It becomes personal. The strongest preventive step depends on why the fracture happened in the first place.
If the tooth had a large old filling, replacement or crown coverage on heavily restored molars may prevent a repeat event. If nighttime grinding is part of the picture, a properly fitted night guard can reduce damaging forces. If the trigger was habitual chewing on ice, hard candy, pens, or popcorn kernels, the behavior itself has to change. No restoration is tougher than enamel under ideal conditions, and even enamel has limits.
Regular exams help, but they are not magic. Dentists can often spot craze lines, worn cusps, failing restorations, and early fractures. They cannot guarantee which tooth will break next. What they can do is identify teeth that are carrying high risk and reinforce them before a meal does the forcing.
Choosing the right emergency care
Not every practice handles urgent cracked-tooth cases the same way. A true Emergency Dentist will focus not just on pain control, but on diagnosis, stabilization, and an honest discussion of next steps. If advanced restoration or root canal care is needed, coordination matters. A smooth handoff between general dentist, emergency provider, and specialist can be the difference between fast resolution and a week of avoidable uncertainty.
When calling for an appointment, it helps to describe the event clearly: what food caused it, whether a piece broke off, whether pain occurs on biting or with temperature, and whether there is swelling. Those details help the office gauge urgency and prepare for the type of treatment you may need.
A cracked tooth after biting hard food can feel random, but it usually is not. There is almost always an underlying vulnerability, a concentrated force, or both. The sooner that combination is assessed and stabilized, the better the odds of keeping the tooth comfortable and functional. Emergency dentistry is at its best in exactly this situation, when quick action can turn a painful surprise into a manageable repair rather than a cascading problem.
Smyle Dental Bakersfield
2016 E St, Bakersfield, CA 93301, United States
+16614939040
FAQ About Emergency Dentist
What counts as a dental emergency?
Severe tooth pain, facial swelling, uncontrolled bleeding, a knocked-out or displaced tooth, and significant dental trauma may need prompt assessment. Trouble breathing or rapidly increasing swelling requires urgent medical help.
What should I do if a permanent tooth is knocked out?
Handle the tooth by the crown rather than the root, keep it moist, and contact a dentist immediately. Fast treatment can improve the chance of saving the tooth.
Can an emergency dentist treat severe tooth pain the same day?
Same-day care may be available depending on the cause and schedule. The dentist will examine the area, may take digital X-rays, and recommend treatment based on the diagnosis.
Should I go to the emergency room for dental swelling?
Seek urgent medical care for trouble breathing, difficulty swallowing, rapidly spreading facial swelling, or other severe symptoms. A dentist can assess the underlying dental cause and provide appropriate follow-up care.
Ends · KAMERONZXBC724